Pain is both a sign and a stressor. In emergency situation treatment, it additionally ends up being a risk factor: absolute discomfort drives tachycardia, raises high blood pressure, clouds evaluation, and can make complex transportation and treatments. Short courses hurting administration, straightened to PUAEME008 Offer discomfort monitoring, exist to develop positive frontline experts who can evaluate, determine, and provide safe analgesia within their extent. Obtaining that right takes more than a pharmacology lecture. It calls for scenario-based judgment, experience with local procedures, and a regimented approach to documentation and client safety.
I have educated, examined, and rejuvenated multiple programs that declare to "provide discomfort monitoring training." The training courses that really change technique tend to share a couple of top qualities. They attach drug options to details client presentations, they drill the operational details that stop working under stress, and they tell the truth about trade-offs. They likewise map meticulously to PUAEME008 so that learners can get a recognised discomfort monitoring certificate, not simply a certification of attendance.
This short article lays out what PUAEME008 calls for in practice, how brief programs suffering management can satisfy the criterion, and exactly how to pick the right discomfort administration program for your duty, whether you are a nurse in immediate care, a paramedic, a physiotherapist handling acute flare-ups, or a medical professional upskilling for remote area work.
What PUAEME008 Really Covers
PUAEME008 Give pain management rests within public safety and security training, and it anchors discomfort pain management certification relief to safe systems of treatment. The device concentrates on short-term, procedural, and acute pain in prehospital and emergency contexts, not long-lasting persistent discomfort. Key elements consist of:
- Accurate evaluation making use of verified pain ranges proper to age and cognitive condition, and duplicated reassessment after interventions. Selection and administration of analgesia within organisational plans, typically consisting of inhaled methoxyflurane, oral analgesics, intranasal fentanyl, or morphine relying on jurisdiction and scope. Monitoring, unfavorable event readiness, and escalation, including management of queasiness, hypotension, respiratory anxiety, and altered sensorium. Documentation that records standard, treatment, feedback, and handover information, and interaction with obtaining teams. Scene and spectator safety and security, consent, and culturally appropriate care.
While the precise medicine list varies by service, the PUAEME008 supply discomfort management structure is medication agnostic. It is about secure systems: evaluate, decide, provide, keep track of, document, and hand over. Any type of reliable give pain administration training course that claims to fulfill PUAEME008 needs to make those actions visible in every scenario.
Why brief programs benefit active clinicians
Time pressure is a real restriction. Devoting to a multi-day program is difficult for shift employees. Short training courses hurting management, normally six to ten hours with combined online and in person elements, supply a functional route to pain monitoring accreditation without endangering professional shifts. When well made, a certificate training course suffering management can deliver focused skills that translate to field efficiency the very same night.
Speed, nevertheless, can not come at the expense of deepness. The best discomfort monitoring training programs equilibrium crisp pre-read content with immersive, hands-on method. If you can complete a training course without ever before taking care of a spacer, putting together a methoxyflurane device, or preparing an intranasal dosage, it is unlikely to construct useful skills.
The core abilities a PUAEME008-aligned program must produce
Every pain monitoring certificate training course straightened to PUAEME008 should demonstrably construct the following competencies:
Pain assessment that survives the noise. A single numeric ranking is not enough. Students need to utilize age-appropriate devices like Wong-Baker faces for youngsters, Behavioral Pain Scale surrogates in the baffled person, and basic questions that cut through the adrenaline of injury scenes. Efficient training courses show you to triangulate: the individual's report, their behavior and physiology, and your mechanism-of-injury intuition.
Safe drug selection within extent. Medicine food selections differ. Country nurses may command for intranasal fentanyl and dental anesthetics, while event medics may count on methoxyflurane alone. Students must practice choice trees that mirror their real methods. For example, a sickly client with a broken neck of femur, nil by mouth, hypotensive at 92/58 and SpO2 95 percent on area air will not endure the exact same plan as a young hill biker with a mid-shaft tibia fracture and stable vitals.
Dose calculation under pressure. Intranasal fentanyl in micograms per kilogram, optimum per nostril volume, redosing intervals, and collective totals are where errors slip in. Excellent training makes use of drills with simulated syringes and atomisers, and forces you to recite your five legal rights aloud. Seeing a person fumble a dose throughout simulation tells me more than any created test.

Adverse impact readiness. Antiemetics for methoxyflurane-induced nausea or vomiting, naloxone protocols for opioid-induced respiratory system clinical depression, additional oxygen, and positioning approaches need to be automated. A program that never ever simulates a drop in breathing rate after fentanyl misses out on the point.
Reassessment and documentation. Discomfort relief is a process, not a one-off act. Learners should chart baseline discomfort, time of administration, dosage, path, result at 5 and ten mins, and any type of side effects. That documentation ends up being a handover shorthand that protects the patient and the clinician.
Medication choices in scope for PUAEME008
Because plans vary by state and solution, a discomfort monitoring certification training course usually provides a common toolbox with neighborhood adjustments. The usual alternatives:
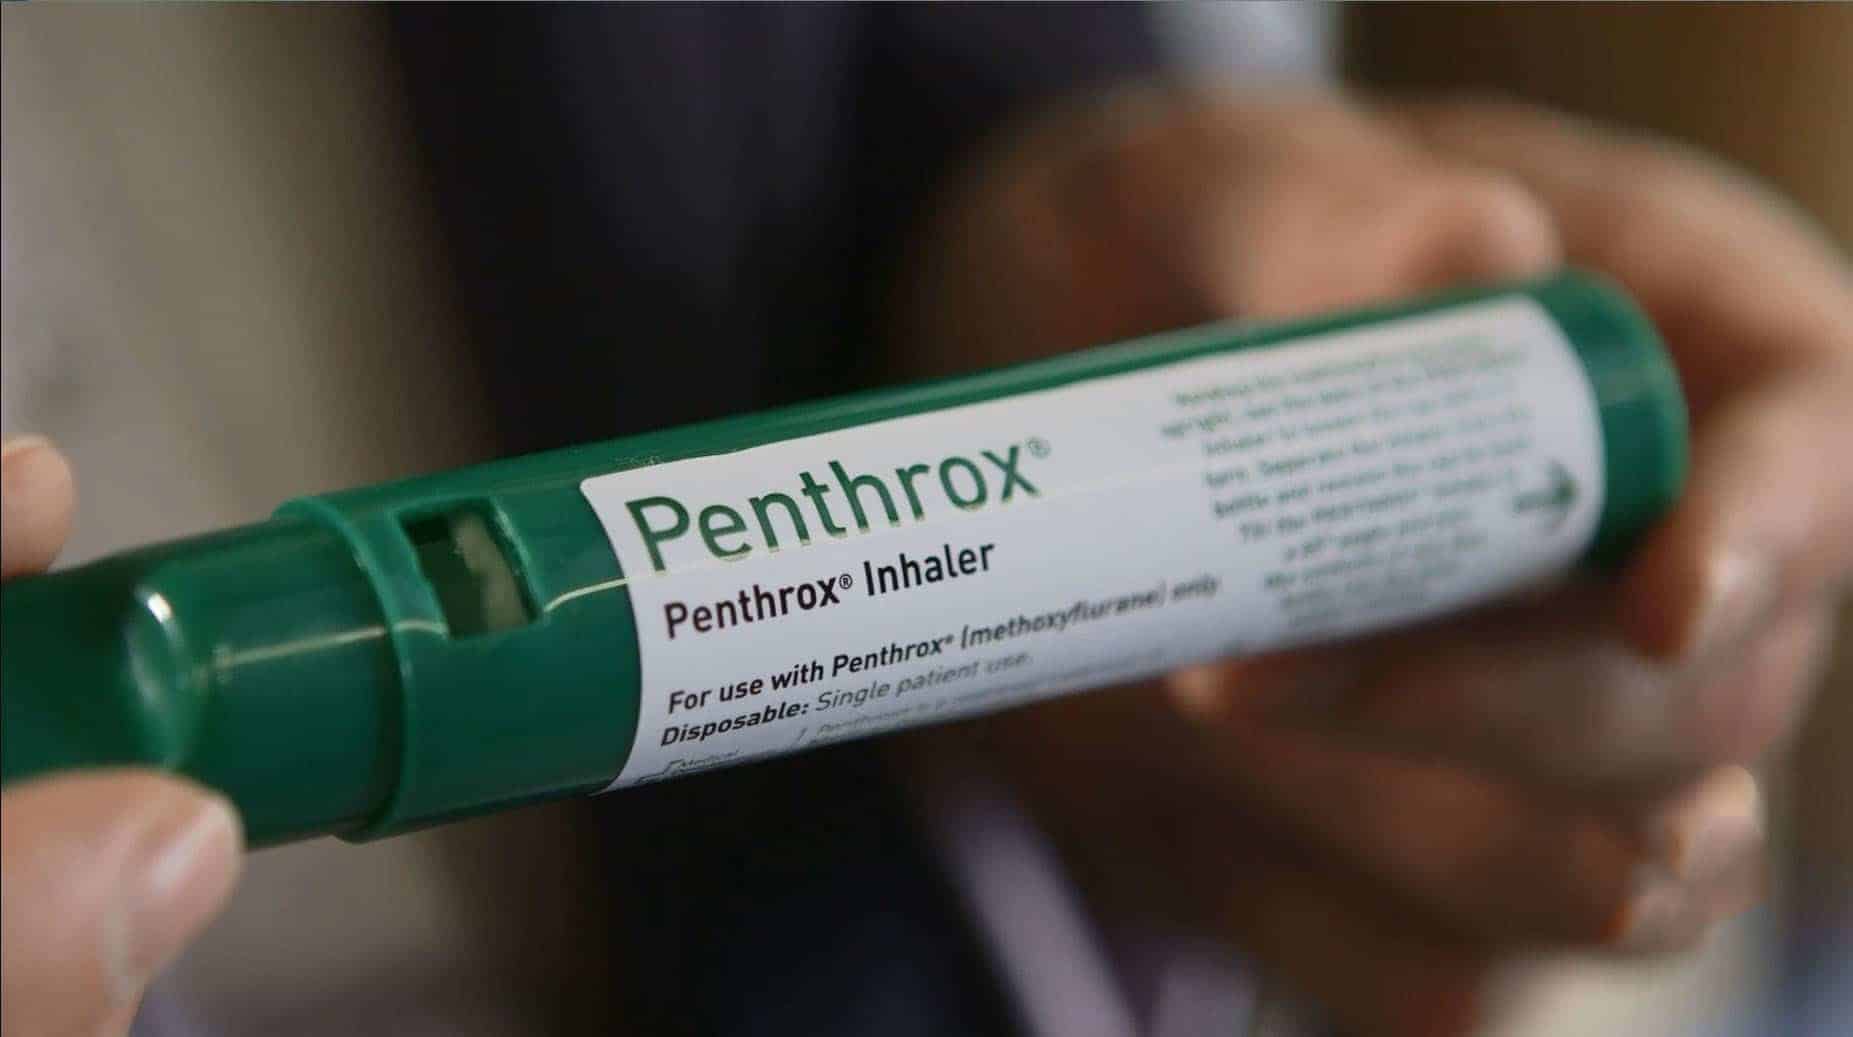
Methoxyflurane. A portable breathed in analgesic made use of commonly in prehospital treatment. It offers fast beginning and patient-controlled dosing. Downsides include dizziness and queasiness, and it is not appropriate for long term use or in clients with specific renal risk profiles. In jampacked scenes, training the person to breathe in and breathe out away from spectators matters more than the majority of students expect. A two-minute training session can make or damage its effectiveness.
Intranasal fentanyl. Fast onset, needle-free, and simple to titrate. It is outstanding for fractures and burns, and aids with anxious youngsters. The dose-volume limitation for the nostrils is a genuine restraint. If you fill the nose beyond regarding 1 millilitre total volume, it trickles rather than atomises, which blunts effect and elevates risk. People learn this just by experimenting atomisers and watching the spray pattern.
Oral anesthetics. Paracetamol and NSAIDs continue to be the foundation of multimodal analgesia. In the area, they are complements that lower opioid demands. The course needs to educate when oral agents aid and when they only include hold-up, such as the nil-by-mouth trauma client awaiting surgery.
Morphine or IV opioids. In some solutions, PUAEME008 learners will not offer IV opioids; in others, they will under guidance. If IV courses are included, cannulation skills are presumed preexisting, and the program should concentrate on titration, monitoring, and documentation instead of cannulation itself.
Adjuncts and regional blocks. A lot of brief courses do not train nerve blocks within PUAEME008, however some services utilize intranasal ketamine or nitrous mixes under different methods. If a training course markets ketamine without extended monitoring web content, ask questions.
A legitimate discomfort monitoring training carrier will release the precise medicine range for their PUAEME008 give discomfort monitoring course and cross-reference to local protocols. Obscure assurances regarding "effective medications" are a red flag.
Building self-confidence through circumstance realism
The class can overemphasise clean lighting and ideal hearing. Genuine scenes rarely cooperate. I once watched a brand-new graduate blow up of a crack splint because he tried to preserve sterility in a muddy paddock while the individual howled. The professional close to him, silently, secured basic convenience initially: a blanket as a splint bolster, a quick analgesic dosage, and after that a safe transfer to stronger ground. No one remembers the pain scale number from that phone call, yet every person bears in mind that the client quit clawing at the leg after the first inhalations.
Effective brief courses in pain monitoring phase these information intentionally. They use background sound, a confined room, or a concerned family member that keeps interrupting. They make you describe to a moms and dad why you are offering an analgesic to a kid with a melt before you start cooling, or how you will time oral paracetamol prior to a lengthy rural transportation. The factor is not to deceive learners however to inoculate them versus typical failing modes: bad communication, hesitation, and loss of sequence.
Documentation that takes on scrutiny
Charts and handovers are commonly the starting point auditors look. A pain administration certificate should feature better documents practices. A strong discomfort management program for nurses, paramedics, and first -responders drills concise phrases that catch scientific thinking. Rather than "offered fentanyl," write "IN fentanyl 60 mcg at 14:12 for L lower arm fracture, discomfort 8/10 to 4/10 at 14:18, no queasiness, RR 16 stable, SpO2 98 percent." That line can be skimmed and relied on. It is likewise defensible months later on when memory fades.
Handing over to the obtaining group, call out the analgesia sequence with dosages and times, any problems with methoxyflurane resistance, last dental drug time, and whether the person continues to be nil by mouth. If your solution allows a second line agent, say whether you considered it and why you held back. Good courses make that specific in debrief.
Tailoring to various specialist roles
The content positioning differs when you instruct pain administration courses for nurses versus pain management training courses for physiotherapists.
For nurses in immediate care or remote centers, discomfort monitoring training for nurses often stresses triage acceleration, standing orders, and paperwork under nurse-led models. The educational program must include double-check systems when working solo, giving guidelines, and communication with on-call clinical police officers. Scenarios must include contending priorities, for example a flustered individual with kidney colic showing up while a clothing change is underway.
For physiotherapists who run into acute flare-ups, a discomfort monitoring accreditation program needs to regard extent. The program might concentrate on screening red flags, instant non-pharmacologic methods, simple oral analgesia assistance where permitted, and safe recommendation. Instructing a physio to trainer paced breathing or to position a back radiculopathy individual for convenience issues greater than medicine drills. Pain management training courses for physiotherapists that meddle sophisticated anesthetics without a clear range declaration can misdirect learners.
For occasion paramedics and initial -responders, PUAEME008 offer discomfort monitoring pain management certificate usually restricts medications to breathed in and oral courses. Scene management, client positioning before transportation, and handling bystander assumptions end up being core abilities. The program ought to consist of crowd-communication scripts, because they reduce conflict when you carry out analgesia in public view.
Non-pharmacologic techniques that really help
Medications are not nearly enough, specifically when transport is postponed or doses are constrained. An all-round pain administration program incorporates strategies that decrease suffering without a milligram being given.
Positioning stays the quiet hero. A client with a proximal humerus crack that is resting screw upright will strain and protect. A straightforward sling and cushion, with the seat delicately reclined, can cut in half the discomfort rating prior to the initial inhalation. Educate trainees to scan for stress factors and readjust assistances. In burns, altitude and mild cooling while maintaining core heat matter; overcooling extends transportation and enhances discomfort.
Communication is analgesia. People that understand what happens next often unwind enough to tolerate the early minutes. A brief script helps: "I am mosting likely to provide you something you take a breath that takes the edge off within a minute. Keep it secured against your mouth and breathe in deeply three times. You manage just how much you take, and you can pause if you really feel lightheaded. I will stick with you and inspect your numbers." Training courses should need students to state those words out loud while setting up the device.
Immobilisation and splinting provide mechanical alleviation. Training has to include improvisated choices for when kits run completely dry: rolled towels, triangular bandages, a folded publication for a wrist. Excellence is the opponent of alleviation. Set splinting exercise with immediate analgesic training to show how the two job together.
Breathing techniques are not simply for antenatal classes. Training slow-moving nasal inhalation with a longer breathe out reduces supportive drive. When teamed with intranasal fentanyl, the strategy frequently steadies the patient sufficient to avoid hyperventilation or breath-holding that postpones atomiser delivery.
Edge cases where judgment matters
No program can manuscript every scenario, yet a PUAEME008-aligned program ought to emerge tricky situations that force trade-offs.
The drunk injury client. Alcohol makes complex opioid usage and masks discomfort. A rigid guideline of "no opioids with alcohol" leaves clients twisting, however laid-back dosing dangers breathing anxiety. Efficient training educates cautious titration with raised observation, choice for inhaled agents if available, and an emphasis on air passage positioning and transportation readiness.
The sickly older grown-up with numerous comorbidities. Age adjustments pharmacodynamics. A small intranasal dosage can generate huge impacts, and methoxyflurane queasiness can cause aspiration risk. A good instructor makes learners rehearse half-doses, slower titration, and very early antiemetic factor to consider. The equilibrium between convenience and safety and security comes to be a discussion with the patient and carer.
The kid that declines to breathe in. Requiring a device to the face backfires. Courses need to teach the different route within scope or show acceleration actions, including topical anaesthetic for IV if allowed, diversion strategies, or a brief delay while a caretaker designs very first puffs. Role-playing this with a doubtful instructor acting as the youngster deserves more than any kind of slide.
The long transport in a warm rescue. Methoxyflurane loses efficiency with tool cooling and leaks. Intranasal representatives may dry nasal mucosa. Preparation a staggered dosage pattern, making sure hydration where secure, and building in keeping track of breaks becomes part of the circumstance. Students should be asked to intend analgesia for a 90-minute rural road, not simply a suv 10-minute sprint.
Assessment, review, and when to escalate
Pain monitoring is vibrant. The initial plan may underperform. Programs that push learners to reassess and pivot develop secure reflexes. If breathed in analgesia provides only low relief, do not maintain going after the very same effect out of practice. Take into consideration a 2nd technique if scope permits, or pair with non-pharmacologic modifications. If an individual's pain gets worse or changes personality, deal with that as new info: reassess for compartment disorder danger, evolving abdominal pathology, or a missed out on injury.

Know your escalation limits. Respiratory rate going down listed below a service-defined floor, SpO2 dropping in spite of oxygen, brand-new complication, or unrestrained throwing up all trigger certain feedbacks. Students have to have those numbers and activities at their fingertips. In programs I run, I need pupils to verbalise an acceleration line, as an example, "If RR dips below 10 or the patient comes to be rousable to voice only, I will certainly cease opioids, sustain the airway, and prepare naloxone per method."
Evidence base without the jargon
Short programs in some cases drown individuals in citations. The proof in prehospital discomfort management, while advancing, sustains a couple of functional realities. Early analgesia enhances patient collaboration, which reduces extrication and enhances procedural success. Multimodal strategies reduce single-agent negative effects. Intranasal routes are safe and effective in different ages when dosed properly. Methoxyflurane gives rapid relief however calls for queasiness planning. Opioid negative events are uncommon with cautious titration and surveillance, however they do occur, and naloxone must be available.
The proof likewise reminds us that documents conformity associates with security. Clinicians that continually record baseline and post-dose pain scores often tend to spot inadequate response earlier. A training course that develops those behaviors is not simply instructing paperwork; it is improving client outcomes.
Choosing a carrier: what to look for
Selecting a pain management accreditation training course is simpler if you concentrate on a few tangible criteria rather than shiny brochures.
- Clear mapping to PUAEME008 Offer pain management, with released understanding results that match the device's components and efficiency criteria. Hands-on experiment the precise devices and delivery courses your solution uses, consisting of methoxyflurane arrangements, atomisers, and spacer strategy if relevant. Qualified instructors with frontline experience who can provide grounded comments, not simply state slides. Assessment that includes observed scenarios, not just multiple-choice tests. Ask whether you will certainly be examined on a full scenario from assessment to handover. Post-course assistance, such as quick-reference cards, dose calculators, and a line of call for method questions.
If you are looking for a pain monitoring certificate to satisfy a credentialing need, validate that the carrier concerns a declaration of achievement that provides PUAEME008. Numerous brief courses in pain administration supply fantastic understanding yet do not honor recognised systems. That is great for professional growth, however it will certainly not fulfill human resources's "discomfort management qualification program" requirement.
How organisations can embed the gains
One-off training discolors unless the office strengthens it. Solutions that obtain value from pain administration training courses do a couple of easy things. They stock the gear in foreseeable locations and sizes, from paediatric atomisers to grown-up cannulas. They add discomfort reassessment prompts to patient care records. They motivate case evaluations where groups go over missed out on analgesia chances without blame. They construct a society where asking for a 2nd set of eyes on a complicated dosing question is applauded, not punished.
A small instance: one center included a brilliant orange sticker to the front of every acute trauma data that reviews "Standard pain score videotaped?" Compliance jumped for the simple reason that the timely showed up at the ideal moment. Training planted the idea; the system made it stick.
A sample training day that meets the standard
Providers organise different timetables, yet a realistic single-day path for a PUAEME008-aligned discomfort monitoring course might appear like this:
- Morning online modules completed prior to participation, covering physiology of pain, pharmacology basics, and system components, 2 to 3 hours. Brief in-person wrap-up and Q&A with neighborhood method focus, 45 minutes. Device terminals turning through methoxyflurane assembly and training, intranasal shipment with dose estimations, and paperwork drills, 90 minutes. Scenario block with three cases per learner: paediatric melt, senior hip crack, and upset inebriated trauma, 2 hours including debriefs that concentrate on judgment and communication. Assessment circumstance and understanding check, 60 to 90 mins, with immediate comments and remediation time where needed. Closing conversation on handover language, adverse occasion escalation strategies, and integrating non-pharmacologic strategies throughout transport, 30 minutes.
That cadence offers sufficient rep to develop muscle mass memory without fatiguing students. The assessment circumstance have to be strenuous, with sensible monitors and time pressure, to reflect area demands.
Where brief courses sit within wider discomfort education
A discomfort monitoring certification course straightened to PUAEME008 is not a fellowship in pain medication, and it must not claim to be. It is a focused credential for emergency situation pain management at the factor of treatment. For medical professionals who want to grow abilities, pathways exist: prolonged extent programs that add ketamine and nitrous, sedation components, or multidisciplinary certificate programs that bridge severe and chronic pain. The factor is to match the training to your duty. Overtraining past range elevates risk if your work environment does not support the added skills.
Physiotherapists who complete an intense care pain management training course could next off pursue training in graded exposure and main sensitisation for chronic conditions. Registered nurses in remote centers might include a step-by-step sedation component or crack management to prolong their capability. The most effective companies will recommend on those paths, not just sell the next course.
The human side of discomfort relief
A final thought from the field. Years back, after a late-night contact us to a farmhouse, we located an older male with a collarbone fracture from a loss. He swung off assistance up until his partner urged. He held up till the first 3 breaths of methoxyflurane, then his eyes softened. He spoke about his pet dog instead of his shoulder. The discomfort was still there, however it was smaller, and that made sufficient room for us to move him, secure the sling, and drive the lengthy crushed rock track without jolting him into a panic. The intervention was basic, well within PUAEME008. The end result relied on prep work, not heroics.
That is what excellent discomfort monitoring training does. It furnishes common medical professionals to supply reliable alleviation under incomplete conditions. It mixes pharmacology, communication, and systems assuming into a repeatable series. And it grants a discomfort administration certificate that represents more than a training course code, due to the fact that the technique behind it is sound.
If you are evaluating pain monitoring training for nurses, physiotherapists, or combined frontline teams, ask to see the scenarios, the tools, the analysis rubric, and the statement of attainment. If they line up with PUAEME008 Offer discomfort administration, and the teachers can chat with the compromises without flinching, you are likely in good hands.